Anion Gap Calculator for Electrolyte Status Review
What the Anion Gap Measures
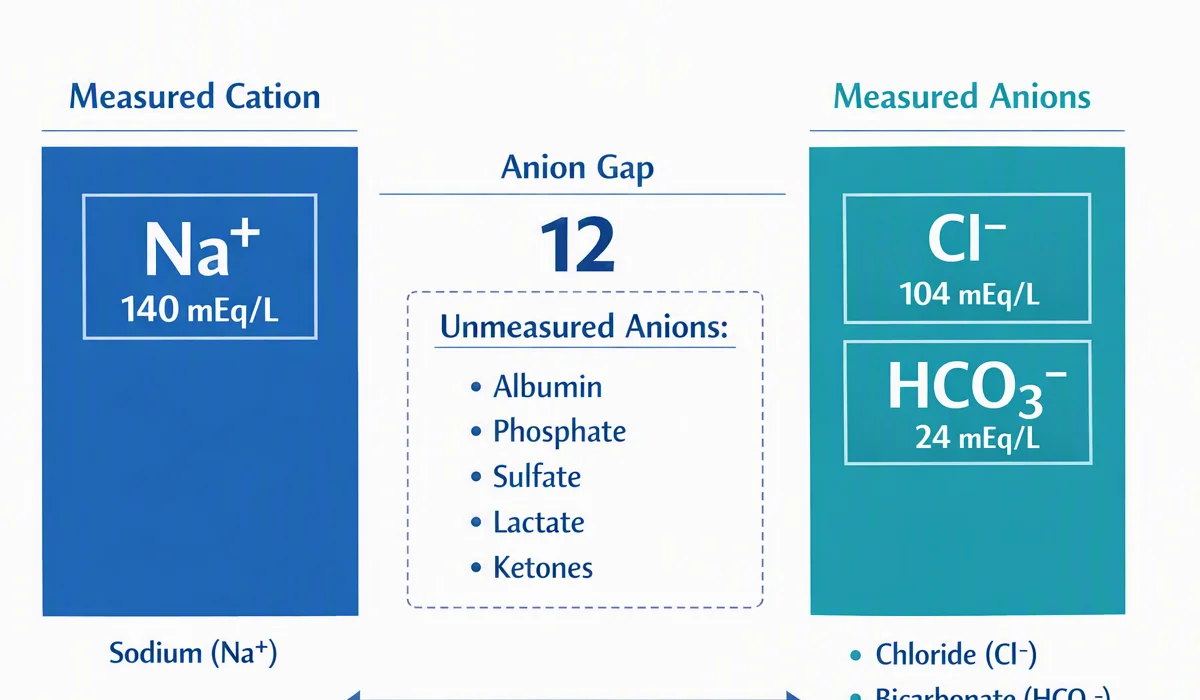
The anion gap is a helpful way to analyze a serum electrolytes test and detect hidden shifts in acid-base balance. It shows the difference between measured cations and measured negatively charged ions in the blood. Because the body maintains electrical neutrality, a discrepancy exists between the ions commonly reported on standard chemistry testing and the unmeasured ions that also contribute to overall charge.
In clinical terms, the anion gap helps clinicians identify a possible metabolic acidosis and reduce the list of likely causes. It is not a isolated diagnosis. Instead, it is a diagnostic aid within broader electrolyte interpretation and laboratory analysis. When paired with the rest of the electrolyte panel, it can reveal whether there is an accumulation of acids, a loss of bicarbonate, or another metabolic disturbance affecting the patient.
The anion gap is particularly helpful because many important acids and their accompanying anions are not directly measured in routine serum chemistry. These unmeasured anions can increase the gap when they accumulate. That is why the anion gap is often used as part of an acid-base evaluation and broader diagnostic framework for suspected acid-base disorders.
How to Work with an Anion Gap Calculator
An Anion Gap Calculator is an easy method to complete anion gap calculation using the standard laboratory values. The calculator typically asks for sodium, chloride, and bicarbonate. Once entered, it calculates the gap and supports immediate clinical assessment of the patient’s electrolyte pattern.
Using the calculator is simple:
- Type in the serum sodium value from the electrolyte panel.
- Type in the serum chloride value.
- Enter the bicarbonate value, often reported as CO2 on chemistry testing.
- Review the calculated anion gap and compare it with the lab’s reference range.
The calculator can serve as a useful interpretation guide, especially when deciding whether a patient’s picture suggests high anion gap metabolic acidosis or a more typical normal anion gap metabolic acidosis. It is also useful when reviewing serial labs, because changing values can show whether a metabolic problem is improving or worsening.
A calculator should be used as a diagnostic aid, not as a replacement for a full evaluation. The number itself matters, but so do the patient’s symptoms, history, medications, and other laboratory values. For example, the same anion gap may mean something different in a patient with vomiting, kidney disease, or suspected toxin exposure.
Formula for Anion Gap and Expected Range
The usual anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some doctors and testing facilities may use variations that include potassium, but the sodium-based formula is the most widely used for everyday assessment. The resulting value reflects the amount of measured cations not accounted for by measured anions and therefore offers information about unmeasured anions.
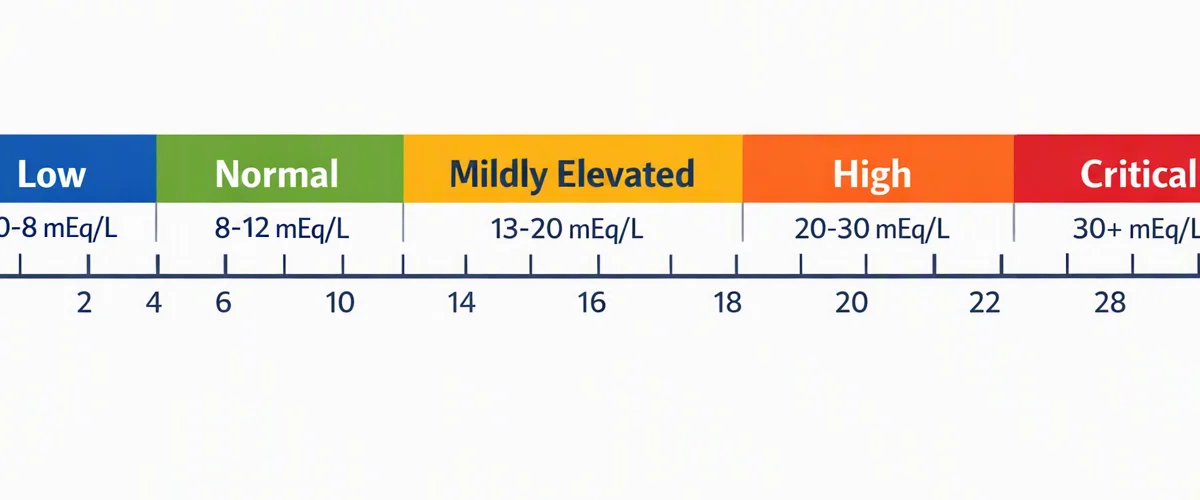
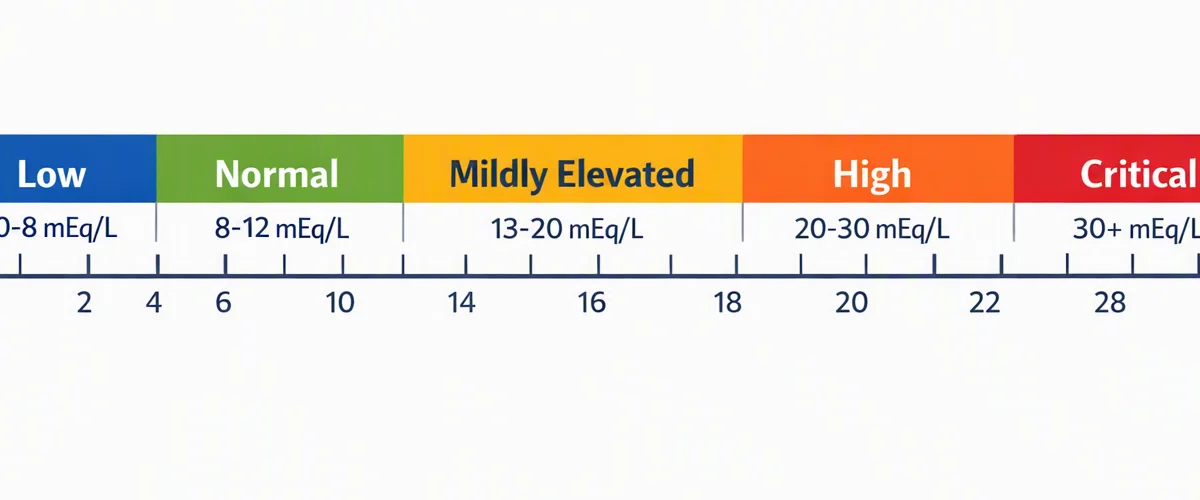
The normal anion gap is not identical in every laboratory. The exact reference range depends on the assay method, analyzer, and lab-specific reporting practices. This is why the calculator result should always be compared with the local range rather than relying on a single universal cutoff. In many settings, the normal range is relatively narrow, and a result above it suggests excess acids or changes in albumin.
Albumin matters because it is a major negatively charged protein in serum and contributes significantly to the expected gap. When serum albumin is lower, the measured anion gap may appear falsely normal or low even if there is an underlying acid-base problem. That is why albumin is an essential part of any careful laboratory analysis of the anion gap.
Interpreting the number also requires understanding the clinical setting. A mildly increased value may suggest early disease, while a much higher value more strongly suggests a significant metabolic acidosis. The calculator provides the number, but the meaning comes from the broader acid-base disorder context.
Corrected Anion Gap in Low Albumin
In cases where serum albumin runs low, the raw anion gap can miss the true acid burden. This is why albumin correction becomes useful. In patients with hypoalbuminemia, the corrected anion gap revises the reported value to more closely represent the underlying chemistry.
The reason for this adjustment is physiologic. Albumin is a major unmeasured anion, so a reduction in albumin lowers the expected anion gap. Without correction, a patient with clinically important acid accumulation may appear to have a normal result. That can lead to missed recognition of an acid-base problem during electrolyte interpretation.
Different formulas may be used for albumin adjustment, but the overall concept is the same: estimate what the anion gap would be if albumin were normal. The corrected value is then compared with the usual reference range. If the corrected result is elevated, it suggests the presence of an acid load even when the uncorrected result looks less impressive.
This step is particularly useful in patients who are critically ill, malnourished, or have chronic disease associated with low protein states. In those settings, a calculator that accounts for albumin helps improve anion gap interpretation and increases the clinical usefulness of the number.
Elevated Anion Gap vs Normal Anion Gap Metabolic Acidosis
One of the anion gap is to distinguish high anion gap metabolic acidosis from normal anion gap metabolic acidosis. Each are types of metabolic acidosis, but they occur through distinct mechanisms and point toward different causes.
In high anion gap metabolic acidosis, additional acids accumulate in the body. Their anions are not regularly measured, so the gap rises. Common examples include lactic acidosis, ketoacidosis, and acid retention from renal failure or uremia. In these cases, the calculator can highlight a problem that might otherwise be overlooked inside a complex electrolyte picture.
In normal anion gap metabolic acidosis, bicarbonate drops but the gap does not rise because chloride often increases to maintain balance. This pattern is also called a hyperchloremic acidosis. It may occur with gastrointestinal bicarbonate loss or renal tubular problems. The key point is that the anion gap stays near the expected level even though the patient still has an acid-base problem.
Separating these patterns is central to acid-base balance assessment. A calculator can rapidly suggest which pathway is more likely, but the final judgment depends on the rest of the lab data and clinical context. That is why a structured diagnostic framework is so useful during metabolic acidosis workup.
Typical Causes of an Increased Anion Gap
An abnormal gap can suggest a wide range of issues. The main causes are often taught as part of a differential diagnosis for acid-base disorders, but the underlying cause should always be compared to the patient’s presentation and test results.
- Ketoacidosis: Observed in diabetic, alcoholic, or starvation states, where ketone acids increase and widen the gap.
- Toxic alcohols: Ingestions involving methanol, ethylene glycol, or related substances can produce a severe high gap and major metabolic disturbance.
- Uremia: Advanced kidney dysfunction can permit acids to collect, contributing to a high gap.
- Salicylates: Overdose can produce mixed acid-base patterns, including an elevated gap.
- Lactic acidosis: Tissue hypoperfusion, sepsis, seizures, or other causes of lactate accumulation can raise the gap substantially.
- Renal failure: Reduced acid excretion and retained organic acids commonly lead to a high anion gap state.
These conditions are significant because they may need immediate treatment. An elevated gap is not a diagnosis by itself, but it is a important clue that something serious https://anion-gap-reference004.opalvector.com/posts/anion-gap-calculator-with-corrected-sodium-how-to-interpret-results is affecting the patient’s acid-base state. In some cases, mixed disorders can blur the picture, which makes systematic analysis even more important.
Stepwise Electrolyte Interpretation
A systematic framework helps get the most from any electrolyte panel. The goal is to move from the numbers to a useful clinical interpretation without overlooking important details. The following stages provide a useful method.
- Step 1: Examine sodium, chloride, and bicarbonate in combination instead of in isolation.
- Step 2: Determine the anion gap using the standard formula or an Anion Gap Calculator.
- Step 3: Match the result with the laboratory’s reference range.
- Step 4: Review serum albumin and decide whether albumin correction is needed.
- Step 5: Determine whether the pattern suggests high anion gap metabolic acidosis or normal anion gap metabolic acidosis.
- Step 6: Evaluate a delta gap when the anion gap is elevated and the bicarbonate is low.
The delta gap can help identify mixed acid-base disorders. If the increase in anion gap is larger or less than expected relative to the decline in bicarbonate, there may be another process present, such as a metabolic alkalosis or an additional non-gap acidosis. This makes the calculation more than a simple number; it becomes part of a larger acid-base evaluation.
Clinical interpretation improves when the anion gap is paired with the full history, physical exam, and other lab findings. For example, a patient with vomiting, dehydration, and ketones may have a different explanation than a patient with renal dysfunction and rising creatinine. The same lab pattern can have very different implications depending on the setting.
When an Anion Gap Result Needs Clinical Correlation
An anion gap number should consistently be interpreted in the full clinical setting. That means looking outside the calculator result and using other data to confirm the suspected diagnosis. Important supporting tests include a blood gas, serum lactate, and assessment of kidney function.
A blood gas helps clarify the acid-base status more completely by showing pH, partial pressure of carbon dioxide, and bicarbonate in a clinical context. Serum lactate can confirm lactic acidosis when tissue hypoperfusion or another cause of elevated lactate is suspected. Kidney function testing helps identify renal failure or uremic acid retention as a possible source of the abnormal gap.
Clinical correlation is especially important when the result does not fit the patient’s condition. A normal gap does not rule out clinically important illness, and a high gap should prompt evaluation for causes such as ketoacidosis, toxic alcohols, salicylates, or other metabolic disturbances. Likewise, low albumin can hide a true abnormality, making the corrected anion gap more informative than the unadjusted number.
In practice, the best anion gap interpretation combines calculator output with a careful review of symptoms, medication exposure, volume status, and other laboratory findings. That combination supports better clinical assessment and more accurate decisions during the metabolic acidosis workup.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to support electrolyte interpretation by quickly estimating the anion gap from routine serum values. It helps identify possible metabolic acidosis, differentiate between high and normal gap patterns, and guide further clinical assessment. It is a helpful diagnostic aid rather than a complete diagnosis on its own.
How is calculated the anion gap from sodium, chloride, and bicarbonate?
Follow the standard formula for anion gap: sodium minus the sum of chloride and bicarbonate. Put another way, anion gap = sodium − (chloride + bicarbonate). This depends on the basic serum chemistry values from the electrolyte panel and is the most common method for routine anion gap calculation.
What is regarded as a normal anion gap?
The expected anion gap depends on the lab’s reported range and the analyzer used. Because methods vary, the reported range should always be checked against the specific laboratory values in front of you. A result inside the local range is generally considered normal, while a result above it may suggest a high-gap process or a need for adjusting for albumin.
Why is corrected the anion gap for low albumin?
You correct the anion gap because blood albumin is a major unmeasured anion. In hypoalbuminemia, the raw value can look falsely low or normal even when a clinically important acid burden is present. Albumin adjustment produces a more accurate corrected anion gap and improves the quality of anion gap interpretation.
What conditions can cause a high anion gap?
Common causes of a high gap include lactate acidosis, ketoacidosis, advanced uremia, renal failure, poisoning by alcohols, and salicylate toxicity. These conditions increase unmeasured anions or reduce acid clearance, leading to elevated anion gap metabolic acidosis. The result should be interpreted with a arterial blood gas, lactate level, and the rest of the clinical picture.